
How do you co-manage sleep apnea patients with a sleep physician?

Co-managing OSA with a sleep physician means each clinician owns a defined slice of the care pathway and documents handoffs in writing. The physician diagnoses with PSG or HSAT, prescribes therapy, and interprets efficacy testing. The dentist evaluates candidacy, fabricates the appliance, titrates, and manages dental side effects. The AADSM co-management protocol, aligned with AASM 2015 guidance updated in 2023, formalizes communication at four checkpoints. Done well, co-management improves outcomes, accelerates reimbursement, and grows referral volume.
Defining Roles Up Front
The AADSM 2018 protocol for co-management of OSA assigns the diagnosis, prescription, and efficacy interpretation to the sleep physician and the candidacy evaluation, fabrication, titration, and dental side effect management to the dentist. Put this in a one-page co-management agreement signed by both providers. Each side should know in advance who orders the efficacy study, who reviews compliance data, and who initiates a change in therapy. Ambiguity is the most common driver of poor outcomes and frustrated patients.
Referral Letter Templates
Your oral health is more important than you might realize. It's not just about having a bright smile, it's about maintaining your overall well-being. Regular dental check-ups, proper brushing and flossing, and a healthy diet can prevent many dental issues.


A high-quality referral letter is the foundation of co-management. Outbound letters from the dental office should include chief complaint, STOP-BANG and Epworth scores, Mallampati grade, neck circumference, BMI, mandibular protrusion range, medical history, current medications, and the specific question for the sleep physician. Inbound letters from medicine should include the PSG or HSAT report, diagnosis, severity, prescription, and any CPAP trial documentation. Use a templated letter to make this routine and fast.
Shared Documentation Requirements
Maintain a shared chart that includes the diagnostic sleep study, physician prescription on practice letterhead, baseline dental examination, fabrication records, titration log with date and protrusive position, efficacy study, and annual follow-up notes. The CMS LCD L33611 audit list requires these documents for every Medicare OAT claim. Many state Medicaid plans and commercial payers mirror these requirements. A complete shared chart is what separates a clean reimbursement from a denied claim.
Who Titrates and Who Interprets
The dentist titrates the appliance based on patient-reported symptom improvement and partner observation. Once the dentist judges titration clinically optimal, the sleep physician orders an HSAT or PSG with the device in place. The physician interprets the efficacy study and communicates the result to the dentist. If residual AHI is unacceptable, the physician and dentist jointly decide whether further titration, combination therapy, or a return to CPAP is appropriate. The dentist never interprets the efficacy study.
Communication Cadence
Four communication checkpoints anchor the year. First at referral when the dentist sends the screening packet. Second at diagnosis when the physician returns the study and prescription. Third after titration when the dentist confirms clinical optimization and requests the efficacy study. Fourth at annual follow-up when both providers reassess. Use secure messaging, fax, or an integrated EHR. Document every communication in both charts to satisfy AADSM and payer audit standards.
Billing Implications
Co-management changes the billing picture significantly. The dentist bills medical insurance for OAT under E0486 with supporting CPT codes for examination, fitting, and titration. The sleep physician bills office visits, the diagnostic study, and the efficacy study separately. Medicare requires the dentist to be enrolled as a DME provider. Commercial payers vary, so verify benefits before each case. Avoid duplicate billing by documenting clearly which provider performed which service.
Building Referral Relationships
Strong referral relationships are built on reliability, speed, and shared outcomes. Visit each sleep physician in person at least once a year, bring case examples, and offer to present at their staff meeting. Send a thank-you letter after every referral and a follow-up summary at the three-month mark. Track your conversion rate from referral to delivered device and share that data with the physician. Sleep physicians refer to dentists who close the loop reliably.
Key Takeaways
- Each provider owns a defined slice of the care pathway documented in a co-management agreement.
- Templated referral letters and shared chart documentation drive clean reimbursement.
- The dentist titrates; the physician interprets efficacy studies and adjusts the prescription.
- Four communication checkpoints anchor the annual care cycle.
- Reliable closure of the referral loop is the strongest driver of repeat referrals.
Frequently Asked Questions
Q: Do I need a written co-management agreement?
A: It is not legally required in most states but is strongly recommended by the AADSM and many malpractice carriers. It clarifies roles, supports audit defense, and accelerates dispute resolution.
Q: What if the sleep physician does not order an efficacy study?
A: Send a templated request with the titration log and the specific clinical question. Most physicians comply once they understand the AASM/AADSM requirement. If they refuse, refer the patient to a physician who will.
Q: How do I document a CPAP trial for severe OSA cases?
A: Obtain a copy of the CPAP prescription, the patient's compliance download if available, and a written statement from the sleep physician documenting intolerance. Medicare requires this for severe OSA OAT coverage.
Q: Can I bill medical insurance without a physician prescription?
A: No. E0486 claims require a physician prescription, a qualifying sleep study, and documentation of CPAP failure or intolerance for severe OSA.
Q: How do I handle a patient whose physician is out of state?
A: Most states allow co-management across state lines for established patients. Verify state board rules and ensure the prescription is valid in the dentist's state.
Final Thoughts
Co-management is not paperwork; it is the clinical infrastructure that makes dental sleep medicine sustainable. Invest in templated communication, a shared chart standard, and quarterly check-ins with your sleep physicians. Train your team to track every referral until closure and to document every interaction. Practices that operationalize the AADSM co-management protocol see higher acceptance rates, better outcomes, and a steady stream of physician-referred patients year after year.

Need help ?
Schedule your initial consultation today and start your journey towards a pain-free, healthier smile. Contact us now!
Blog Suggestions
What is the workflow for fitting a SomnoMed appliance, from impression to delivery?
Fitting a SomnoMed appliance follows a predictable workflow: consultation, records, bite registration, lab prescription, delivery, titration, and efficacy testing.
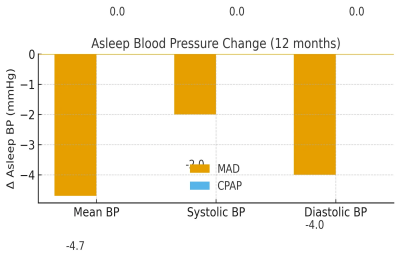
How do iTero intraoral scans improve oral appliance accuracy?
iTero intraoral scans capture the dentition in a digital STL or PLY file with 20 to 50 micron resolution, far tighter than conventional PVS impressions.
What follow-up schedule should you use for oral appliance therapy patients?
Follow the AADSM cadence: a one-week delivery check, one-month titration, three-month efficacy sleep test, six-month stabilization, and annual recalls thereafter.
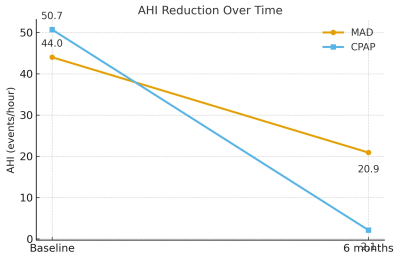
How do you bill medical insurance for a sleep apnea oral appliance?
Billing medical insurance for a sleep apnea oral appliance starts with HCPCS E0486 supported by an LMN, the qualifying sleep study, a prescription, and a face-to-face encounter.